
In this chapter
This chapter answers one question: what can a UAE dental clinic afford to pay to acquire a new paid case, and why does a higher treatment fee not guarantee better acquisition economics? No public UAE dataset was found that reports dental cost per lead, show rates or case acceptance, so the chapter works through four ONS planning models with stated, hypothetical inputs. In those illustrations the aligner course returns the most contribution and the paediatric first visit the least, and the paediatric result turns negative if its receipt is replaced with the single first-visit fees published by two clinics (True Smile, 2026; DentalDate, 2026).
In brief
The four ONS models (implant case, aligner course, veneer case, paediatric first visit) are illustrations with hypothetical inputs, not observed clinic results or market data.
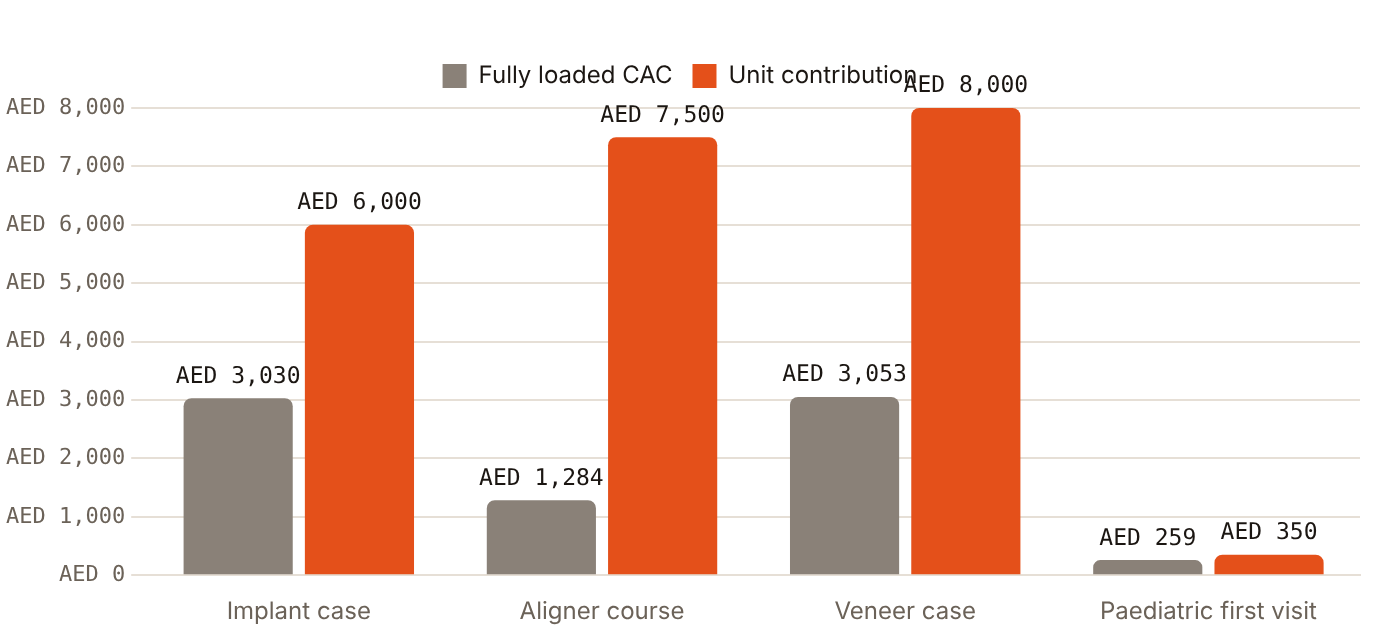
On those inputs the expected paid starts are 8.58 implant cases, 18.69 aligner courses, 7.86 veneer cases and 54.05 paediatric first visits, and fully loaded acquisition cost per paid start is AED 3,030, AED 1,284, AED 3,053 and AED 259.
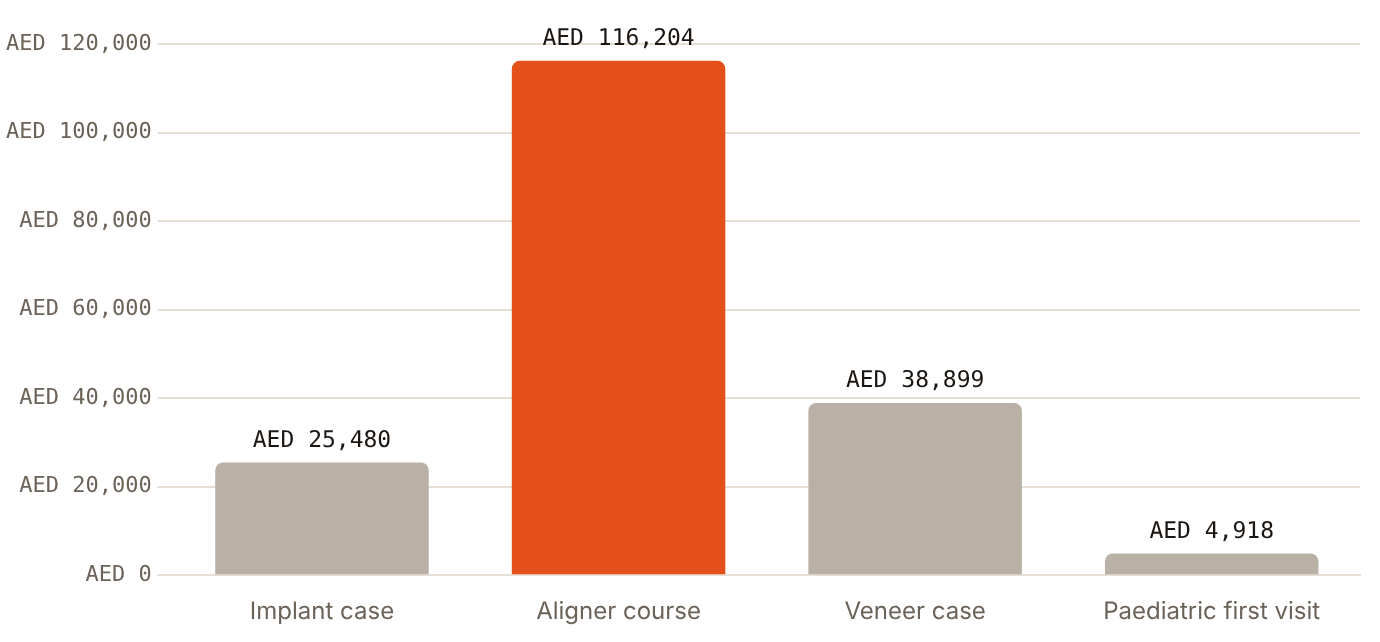
Contribution after acquisition is AED 25,480 (implant), AED 116,204 (aligner), AED 38,899 (veneer) and AED 4,918 (paediatric first visit), before fixed overhead and tax.
Selected published single-provider prices sit near some of the hypothetical receipts: True Smile, Abu Dhabi, lists implant placement at AED 5,500 to 6,500 plus an implant-supported crown at AED 5,000, and DentalDate, Dubai, lists aligners from AED 18,000.
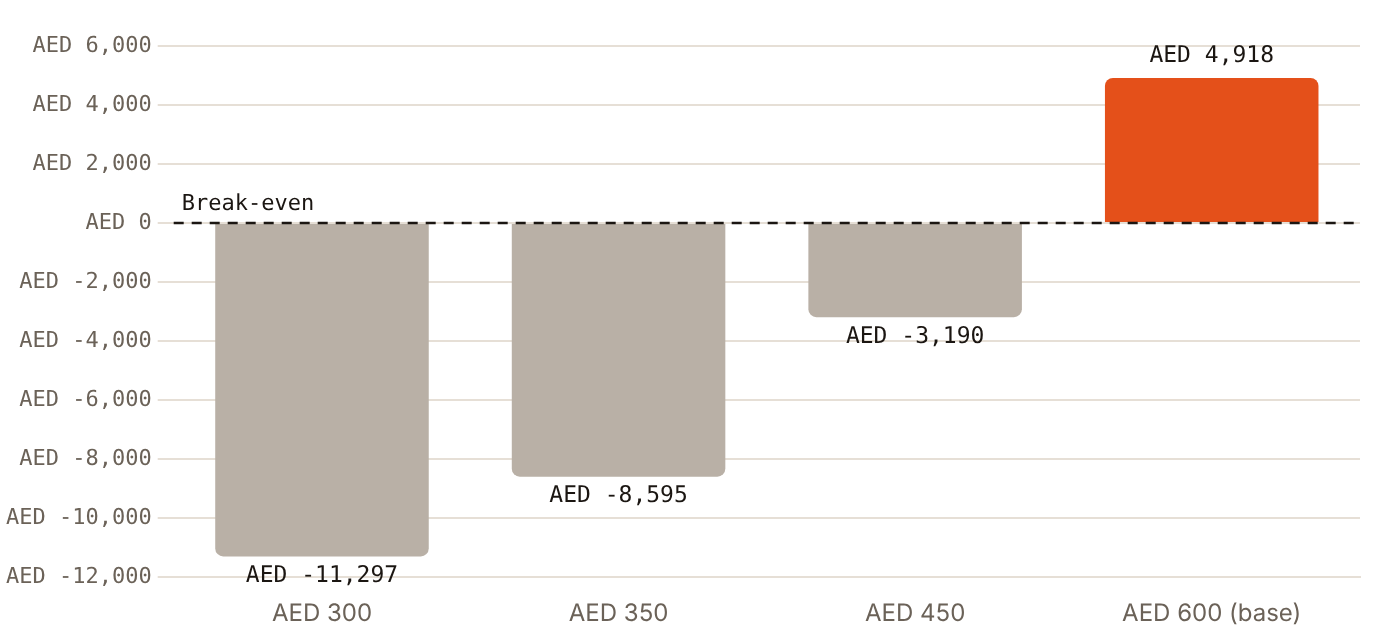
Two published paediatric first-assessment fees are AED 300 (True Smile, Abu Dhabi; DentalDate, Dubai). At a receipt of AED 300 the paediatric model loses AED 11,297.
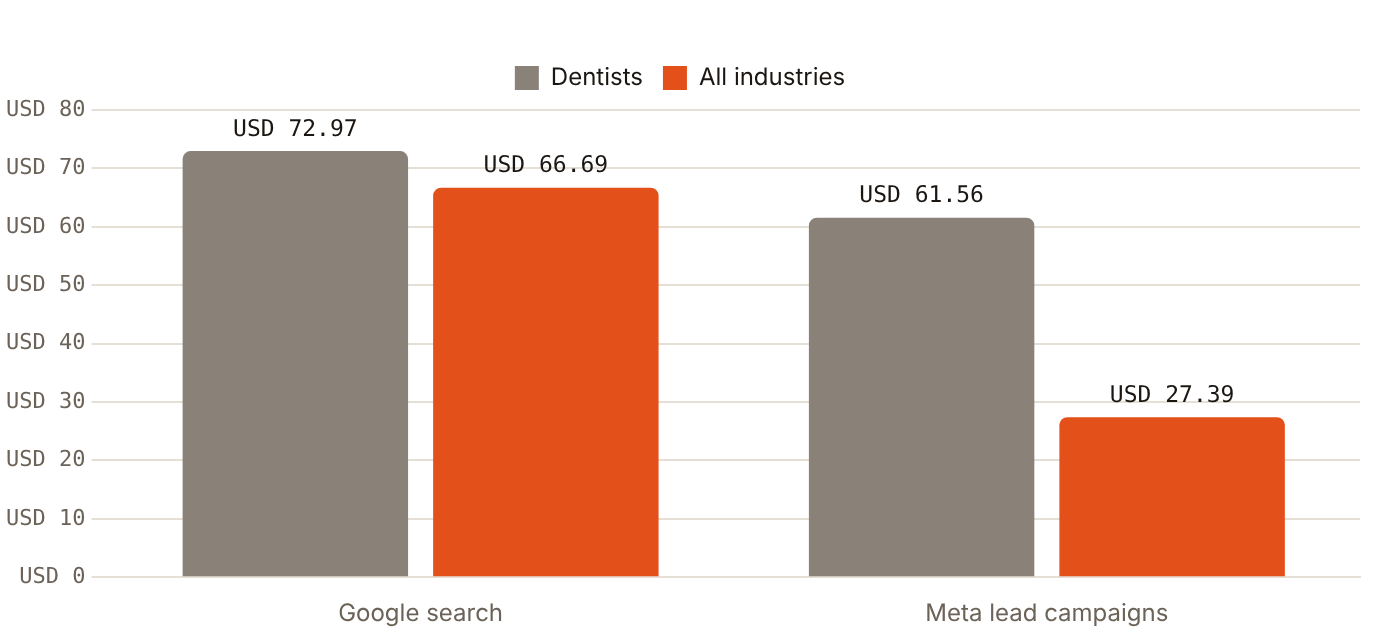
US benchmarks are context only: in 2026 WordStream/LocaliQ data, the US dental median Google search CPL was USD 72.97 and the Meta lead-campaign CPL for dentists was USD 61.56.
The only UAE dental missed-appointment study found reported 22.5% at two private clinics, published in 2011.
Elective cosmetic treatment is standard-rated for VAT at 5% unless prescribed to treat or prevent a condition, so cosmetic receipts should be modelled net of VAT (PwC Middle East, Jan 2018; Gulf News).
What the ONS planning models are, and what they are not
ONS built four acquisition models to show how fee level, delivery cost and conversion interact. Each describes one hypothetical cohort of enquiries funded by one period's acquisition spend, followed through to clinically eligible, paid treatment starts. The service units differ on purpose: the implant and veneer models use a case, the aligner model uses a course and the paediatric model uses a first visit. They are not alternative forecasts for one clinic, and they are not quotations.
Every input is a planning assumption. None was converted from a US benchmark and none is claimed to be an observed UAE result. Rates are the share of the previous stage that moves to the next stage. Money is in AED. The output is contribution after acquisition: collected receipts less variable delivery cost, media and other acquisition cost. Rent, general overhead, financing and tax are excluded, so contribution is not net profit.
ONS reading The models are meant to be overwritten. Their value is the structure: each stage has a denominator, so a clinic can see which assumption carries the result. A clinic that replaces the inputs with its own attended, eligible and paid counts gets a decision tool. A clinic that keeps the illustrative inputs gets only an example.
Hypothetical inputs
| Input (per cohort) | Implant case | Aligner course | Veneer case | Paediatric first visit | Source |
|---|---|---|---|---|---|
| Media spend, AED | 20,000 | 18,000 | 18,000 | 10,000 | ONS planning model, hypothetical [ONS] |
| Cost per click, AED | 30 | 22 | 25 | 12 | ONS planning model, hypothetical [ONS] |
| Click to enquiry | 8% | 10% | 8% | 14% | ONS planning model, hypothetical [ONS] |
| Enquiry qualified | 75% | 80% | 70% | 85% | ONS planning model, hypothetical [ONS] |
| Qualified to booked | 65% | 70% | 65% | 75% | ONS planning model, hypothetical [ONS] |
| Booked to attended | 80% | 85% | 80% | 85% | ONS planning model, hypothetical [ONS] |
| Attended to clinically eligible | 75% | 80% | 75% | 95% | ONS planning model, hypothetical [ONS] |
| Eligible to paid start | 55% | 60% | 50% | 90% | ONS planning model, hypothetical [ONS] |
| Collected receipt per paid start, AED | 12,000 | 18,000 | 16,000 | 600 | ONS planning model, hypothetical [ONS] |
| Variable delivery cost per paid start, AED | 6,000 | 10,500 | 8,000 | 250 | ONS planning model, hypothetical [ONS] |
| Other acquisition cost, AED (content, call handling, tools) | 6,000 | 6,000 | 6,000 | 4,000 | ONS planning model, hypothetical [ONS] |
The inputs are not market averages. The paediatric eligibility rate of 95% and paid rate of 90% reflect that a first visit is usually completed once attended, while implant, aligner and veneer starts depend on assessment, suitability and a patient decision. The aligner course carries the highest receipt and also the highest delivery cost, because laboratory work, aligner sets, refinements and retention fall inside a course.
The formulas
Every derived number in this chapter comes from the formulas below, recomputed for this edition from the stated inputs. Expected starts can be fractional because this is a probability model. Break-even starts are rounded up to whole cases or visits.
| Output | Formula | Implant worked example | Source |
|---|---|---|---|
| Clicks | Media / CPC | 20,000 / 30 = 666.67 | ONS calculation [ONS] |
| Enquiries | Clicks x click-to-enquiry rate | 666.67 x 0.08 = 53.33 | ONS calculation [ONS] |
| Qualified, booked, attended, eligible | Previous stage x stage rate | 53.33 x 0.75 = 40.00; x 0.65 = 26.00; x 0.80 = 20.80; x 0.75 = 15.60 | ONS calculation [ONS] |
| Paid starts | Eligible x paid rate | 15.60 x 0.55 = 8.58 | ONS calculation [ONS] |
| Unit contribution | Receipt minus delivery cost | 12,000 minus 6,000 = 6,000 | ONS calculation [ONS] |
| Media cost per enquiry | Media / enquiries | 20,000 / 53.33 = 375.00 | ONS calculation [ONS] |
| Media CAC | Media / paid starts | 20,000 / 8.58 = 2,331.00 | ONS calculation [ONS] |
| Fully loaded CAC | (Media + other acquisition) / paid starts | 26,000 / 8.58 = 3,030.30 | ONS calculation [ONS] |
| Contribution after acquisition | Paid starts x unit contribution, minus media, minus other | 8.58 x 6,000 = 51,480; minus 26,000 = 25,480 | ONS calculation [ONS] |
| Break-even paid starts | Round up ((media + other) / unit contribution) | 26,000 / 6,000 = 4.33, rounded up to 5 | ONS calculation [ONS] |
| Break-even media cost per enquiry | (Paid starts x unit contribution, minus other) / enquiries | (51,480 minus 6,000) / 53.33 = 852.75 | ONS calculation [ONS] |
The break-even media cost per enquiry is the highest media cost per enquiry the cohort could absorb, with every downstream rate unchanged, before contribution after acquisition reaches zero. It is a ceiling for planning, not a target. If the clinic's real downstream rates are lower than the illustration, the ceiling falls with them.
Funnel volumes in the four illustrations
| Stage | Implant case | Aligner course | Veneer case | Paediatric first visit | Source |
|---|---|---|---|---|---|
| Clicks | 666.67 | 818.18 | 720.00 | 833.33 | ONS calculation [ONS] |
| Enquiries | 53.33 | 81.82 | 57.60 | 116.67 | ONS calculation [ONS] |
| Qualified enquiries | 40.00 | 65.45 | 40.32 | 99.17 | ONS calculation [ONS] |
| Bookings | 26.00 | 45.82 | 26.21 | 74.38 | ONS calculation [ONS] |
| Attended | 20.80 | 38.95 | 20.97 | 63.22 | ONS calculation [ONS] |
| Clinically eligible | 15.60 | 31.16 | 15.72 | 60.06 | ONS calculation [ONS] |
| Paid starts | 8.58 | 18.69 | 7.86 | 54.05 | ONS calculation [ONS] |
| Paid starts per enquiry | 16.1% | 22.8% | 13.6% | 46.3% | ONS calculation (paid / enquiries) [ONS] |
Six stages sit between an enquiry and a paid implant start. Multiplying the six illustrative rates gives 16.1% of enquiries becoming paid implant cases, a little under one enquiry in six. A clinic that judges its implant marketing on enquiries alone is therefore looking at a number five or six steps removed from revenue. The veneer illustration is lower still at 13.6%, because its qualification and paid rates are the lowest of the four.
Economic results
| Result (AED unless stated) | Implant case | Aligner course | Veneer case | Paediatric first visit | Source |
|---|---|---|---|---|---|
| Unit contribution (receipt minus delivery) | 6,000 | 7,500 | 8,000 | 350 | ONS calculation [ONS] |
| Media cost per enquiry | 375.00 | 220.00 | 312.50 | 85.71 | ONS calculation [ONS] |
| Media CAC | 2,331 | 963 | 2,289 | 185 | ONS calculation [ONS] |
| Fully loaded CAC | 3,030 | 1,284 | 3,053 | 259 | ONS calculation [ONS] |
| Fully loaded CAC as share of receipt | 25.3% | 7.1% | 19.1% | 43.2% | ONS calculation [ONS] |
| Fully loaded CAC as share of unit contribution | 50.5% | 17.1% | 38.2% | 74.0% | ONS calculation [ONS] |
| Collected receipts from cohort | 102,960 | 336,489 | 125,798 | 32,431 | ONS calculation (paid x receipt) [ONS] |
| Contribution after acquisition | 25,480 | 116,204 | 38,899 | 4,918 | ONS calculation [ONS] |
| Contribution per AED 1 of acquisition spend | 0.98 | 4.84 | 1.62 | 0.35 | ONS calculation (contribution / (media + other)) [ONS] |
| Break-even paid starts | 5 | 4 | 3 | 40 | ONS calculation [ONS] |
| Break-even media cost per enquiry | 852.75 | 1,640.27 | 987.83 | 127.87 | ONS calculation [ONS] |
In the ONS illustrations the aligner course returns AED 116,204 after acquisition, the paediatric first visit AED 4,918
Contribution after acquisition per hypothetical cohort, AED, before fixed overhead and tax. ONS planning model, hypothetical inputs, not market data
View chart data
| Label | Contribution after acquisition (AED) |
|---|---|
| Implant case | 25480 |
| Aligner course | 116204 |
| Veneer case | 38899 |
| Paediatric first visit | 4918 |
The veneer case has the highest unit contribution of the four (AED 8,000), yet its fully loaded CAC (AED 3,053) is the highest and it produces the fewest paid starts (7.86). The aligner course has a lower unit contribution (AED 7,500) but more than twice as many paid starts (18.69), because every one of its illustrative funnel rates is higher. That is the central point of the chapter: the fee on a price list does not decide acquisition economics. The full funnel does.
The implant model shows a second pattern. Its acquisition cost absorbs 50.5% of unit contribution, against 17.1% for the aligner course. A modest change in implant conversion therefore moves contribution much more than the same change in aligner conversion.
Fully loaded CAC takes 74.0% of the paediatric unit contribution and 17.1% of the aligner unit contribution
Fully loaded CAC and unit contribution per paid start, AED. ONS planning model, hypothetical inputs, not market data
View chart data
| Label | Fully loaded CAC (AED) | Unit contribution (AED) |
|---|---|---|
| Implant case | 3030 | 6000 |
| Aligner course | 1284 | 7500 |
| Veneer case | 3053 | 8000 |
| Paediatric first visit | 259 | 350 |
How much room each model has
A useful way to read a planning model is to ask how far one input could move, with all others unchanged, before contribution after acquisition reaches zero. The table gives three such limits. Formulas: maximum CPC = (paid starts x unit contribution, minus other acquisition cost) / clicks; minimum eligible-to-paid rate = (media + other) / (eligible x unit contribution); minimum receipt = delivery cost + (media + other) / paid starts.
| Break-even limit (one input moved, others fixed) | Implant case | Aligner course | Veneer case | Paediatric first visit | Source |
|---|---|---|---|---|---|
| Maximum CPC, AED (input in brackets) | 68.22 (30) | 164.03 (22) | 79.03 (25) | 17.90 (12) | ONS calculation [ONS] |
| Minimum eligible-to-paid rate (input in brackets) | 27.8% (55%) | 10.3% (60%) | 19.1% (50%) | 66.6% (90%) | ONS calculation [ONS] |
| Minimum receipt per paid start, AED (input in brackets) | 9,030 (12,000) | 11,784 (18,000) | 11,053 (16,000) | 509 (600) | ONS calculation [ONS] |
The paediatric first visit has the least room. Its CPC could rise from AED 12 to AED 17.90 before contribution reaches zero, and its receipt could fall only from AED 600 to AED 509. The aligner course could absorb a CPC above AED 164 on these inputs, but that headroom depends on a receipt of AED 18,000 being collected in full and on a delivery cost of AED 10,500 covering the whole course.
Four single-input stress tests
| Contribution after acquisition, AED, when one input changes | Implant case | Aligner course | Veneer case | Paediatric first visit | Source |
|---|---|---|---|---|---|
| Base case | 25,480 | 116,204 | 38,899 | 4,918 | ONS calculation [ONS] |
| CPC 50% higher | 8,320 | 69,469 | 17,933 | -1,388 | ONS calculation [ONS] |
| Eligible-to-paid rate 10 points lower | 16,120 | 92,836 | 26,319 | 2,816 | ONS calculation [ONS] |
| Attendance rate 10 points lower | 19,045 | 99,709 | 31,037 | 2,693 | ONS calculation [ONS] |
| Delivery cost 20% higher | 15,184 | 76,947 | 26,319 | 2,216 | ONS calculation [ONS] |
A 50% rise in CPC cuts implant contribution from AED 25,480 to AED 8,320 and turns the paediatric model negative at AED -1,388. A 20% rise in delivery cost removes more contribution from the aligner course (AED 39,257) than any other single change except the CPC rise, because the course carries the largest delivery cost. Laboratory fees, refinements and extra visits are therefore as much a marketing question as a clinical one.
The paediatric first visit and the receipt question
The paediatric model uses a hypothetical receipt of AED 600 per first visit. Published first-assessment fees found in this research are lower: True Smile, Abu Dhabi, lists a primary paediatric examination at AED 300, DentalDate, Dubai, lists a first dental visit for children at AED 300, and Emirates Specialty Hospital, Dubai Healthcare City, lists a kids basic package (consultation, cleaning, fluoride) at AED 350 with VAT and age limit not stated. These are single-provider observations, not a UAE price.
| Receipt per first visit, AED | Unit contribution, AED | Contribution after acquisition, AED | Break-even paid visits | Source |
|---|---|---|---|---|
| 300 | 50 | -11,297 | 280 | True Smile; DentalDate ONS calculation; receipt level matches [ONS] |
| 350 | 100 | -8,595 | 140 | Emirates Specialty Hospital ONS calculation; receipt level matches [ONS] |
| 450 | 200 | -3,190 | 70 | ONS calculation [ONS] |
| 600 | 350 | 4,918 | 40 | ONS calculation (base case) [ONS] |
The paediatric illustration turns negative below a receipt of AED 509; at AED 300 it loses AED 11,297
Contribution after acquisition, AED, at four receipts per first visit, other inputs unchanged. ONS planning model, hypothetical inputs
View chart data
| Label | Contribution after acquisition (AED) |
|---|---|
| AED 300 | -11297 |
| AED 350 | -8595 |
| AED 450 | -3190 |
| AED 600 (base) | 4918 |
Paediatric acquisition can still be sound. The reason to run it is usually a family relationship and later preventive care, not the first fee. The evidence for that later value is thin in the UAE. A paediatric dentist quoted by Gulf News suggested budgeting about AED 3,000 a year per child without insurance, said of children whose teeth are well maintained, and an insurer executive put children's preventive care at about AED 800 to 2,000 a year (Gulf News). These are expert estimates, not observed retention.
ONS reading Do not add assumed lifetime value to the paediatric model to make it pass. US vendor arithmetic of a patient lifetime value of USD 6,500, built from one average spend figure and an assumed 10-year relationship, shows how quickly an assumption can justify any budget [Estimate]. Follow actual children through recall visits for a year, then add the observed follow-up value to the model. Until then, judge paediatric campaigns on first-visit economics and attendance.
How the hypothetical inputs compare with published evidence
The receipts in the models were not taken from any price list. The comparison below shows only that they sit inside the range of what selected providers publish, so that a reader can judge whether the illustration is plausible. Prices are single-provider observations with the basis stated; VAT, validity and inclusions are as published (True Smile, 2026; DentalDate, 2026).
| Model unit | Hypothetical receipt | Published reference (provider, emirate, basis) | Grade | Source |
|---|---|---|---|---|
| Implant case | AED 12,000 [ONS] | True Smile, Abu Dhabi: Straumann implant placement AED 5,500 to 6,500 plus implant-supported crown AED 5,000, separate line items (sum AED 10,500 to 11,500, components only) | [Platform] | True Smile |
| Implant case | AED 12,000 [ONS] | The Dome MedDental, JLT, Dubai: implant from AED 6,160 plus implant crown from AED 3,850, plus 5% VAT | [Platform] | The Dome MedDental Clinic |
| Implant case | AED 12,000 [ONS] | Expert estimate, UAE-wide: implant with restoration AED 5,000 to 15,000 per tooth | [Industry] | Gulf News |
| Aligner course | AED 18,000 [ONS] | DentalDate, Dubai: aligners from AED 18,000 per programme | [Platform] | DentalDate |
| Aligner course | AED 18,000 [ONS] | True Smile, Abu Dhabi: Invisalign Lite AED 16,000 to 18,000; Comprehensive AED 23,000 to 27,000 per course | [Platform] | True Smile |
| Aligner course | AED 18,000 [ONS] | Truly Dental, Dubai: Invisalign Lite AED 19,950; Comprehensive AED 24,000 per programme | [Platform] | Truly Dental |
| Veneer case | AED 16,000 [ONS] | Thumbay Dental Hospital, Ajman: Emax veneer smile package AED 14,000, tooth count unspecified | [Platform] | Thumbay Dental Hospital |
| Veneer case | AED 16,000 [ONS] | True Smile, Abu Dhabi: porcelain veneer AED 4,500 per listed veneer | [Platform] | True Smile |
| Veneer case | AED 16,000 [ONS] | VPM International, Ajman: veneers 6 upper and 6 lower, 12,000 rack and 5,000 Ajman Bank member price, currency and date not stated | [Platform] | VPM International Healthcare |
| Paediatric first visit | AED 600 [ONS] | True Smile, Abu Dhabi, and DentalDate, Dubai: first paediatric examination or visit AED 300 each | [Platform] | True Smile; DentalDate |
The implant receipt of AED 12,000 is above the sum of True Smile's published placement and crown components, and the veneer receipt of AED 16,000 assumes several units per case. A clinic using the model should enter its own average collected receipt for the defined case, net of discounts, refunds and insurer adjustments, rather than a list price.
External benchmarks: what they can and cannot tell a UAE clinic
No independent UAE dental CPC or CPL benchmark was found (Admoon, 2024). The only Dubai dental CPC figures are agency claims with no method, for example AED 12 to 18 for "emergency dentist dubai" and AED 10 to 15 for "veneers dubai" (Admoon, 2024). A separate agency estimate puts Dubai healthcare CPC at AED 5 to 15 with no dental split (Enrich Labs, 2025). The hypothetical CPCs in the ONS models (AED 12 to 30) were not derived from either.
| US benchmark, 2026 edition | Dentists | All industries | Geography and period | Source |
|---|---|---|---|---|
| Google search CPC, USD | 8.00 | 5.42 | US, Apr 2025 to Mar 2026 | WordStream / LocaliQ; WebTonic [Industry] |
| Google search conversion rate | 10.67% | n/a | US, Apr 2025 to Mar 2026 | WordStream / LocaliQ [Industry] |
| Google search CPL, USD | 72.97 | 66.69 | US, Apr 2025 to Mar 2026 | WordStream / LocaliQ; WebTonic citing WordStream [Industry] |
| Meta lead campaign CTR | 1.62% | 2.70% | US, 2026 edition (updated 23 Sep 2026) | Search Engine Land citing WordStream by LocaliQ [Industry] |
| Meta lead campaign CPC, USD | 5.70 | 1.80 | US, 2026 edition | Search Engine Land citing WordStream by LocaliQ [Industry] |
| Meta lead campaign conversion rate | 6.07% | 8.54% | US, 2026 edition | Search Engine Land citing WordStream by LocaliQ [Industry] |
| Meta lead campaign CPL, USD | 61.56 | 27.39 | US, 2026 edition | Search Engine Land citing WordStream by LocaliQ [Industry] |
US dentists' 2026 benchmark CPL was USD 72.97 on Google search and USD 61.56 on Meta lead campaigns
Cost per lead, USD, dentists vs all industries. US only, WordStream/LocaliQ 2026 editions. Not UAE data
View chart data
| Label | Dentists (USD) | All industries (USD) |
|---|---|---|
| Google search | 72.97 | 66.69 |
| Meta lead campaigns | 61.56 | 27.39 |
The WordStream search sample covered 13,474 US campaigns across all industries, and the publisher describes its category figures as medians. A "conversion" in that data is a recorded lead or action, not a paid patient (WordStream / LocaliQ, 2025). Dividing a median CPC by a median conversion rate does not have to reproduce the median CPL, so the three figures should not be combined into a funnel. The Meta CPL for dentists is more than twice the all-industry figure in the 2026 edition (Search Engine Land citing WordStream by LocaliQ, 2025).
Vendor compilations offer further US figures with weak sourcing: cost per booked patient of USD 150 to 200 for general dentistry and USD 350 to 500 for implants or cosmetic work, clear aligner consults leading to treatment at about 65%, and new-patient phone calls converting to bookings at 53% on average (WebTonic citing CUFinder; Gaidge, 2025). They are listed so that readers recognise them when quoted, not as inputs.
For UAE marketersA US CPL is not a UAE acquisition cost and a US conversion rate is not a paid-start rate. The ONS break-even media cost per enquiry (AED 852.75 for the implant illustration) is the more useful planning number, because it already carries the clinic's own downstream rates [ONS].
Attendance, response and the middle of the funnel
The ONS models assume 80% to 85% of bookings attend. The only UAE dental study found reported an average missed-appointment rate of 22.5%, from 155 patients and 50 dentists at two private clinics, published in 2011, with fear of pain and emergencies the most cited reasons. A vendor claims clinics in Saudi Arabia, the UAE and Egypt report no-show rates of 20% to 30%, without a source (Thikaa, 2026). The 10-point attendance stress test above shows what such a gap costs: AED 6,435 of implant contribution in the illustration.
Response speed matters before the booking. Cross-industry US studies dated circa 2007 to 2011, quoted second-hand, found leads contacted within 5 minutes 9 times more likely to convert than at 30 minutes (Viva). UAE residents favour WhatsApp: in a 2024 YouGov survey for Zbooni, 65% had used WhatsApp to enquire about a product or service in the past year, against 55% for call centres and 48% for email, and 87% preferred a real person to a chatbot (Communicate Online, early 2024; Communicate). The survey covered all sectors, not dentistry.
Dental anxiety affects the attended and paid stages. In Dubai, 72.3% of 206 adult oral-surgery patients reported moderate or high anxiety, and in a UAE postgraduate dental hospital 22.4% of children self-reported severe dental anxiety while parents reported 33.3% (Alansaari et al., IJERPH 20; AlGharebi, Al-Halabi, Kowash et al., European Archives of Paediatric Dentistry 22:29-40, 2021). Neither study measured booking behaviour, but both suggest attendance support is part of acquisition.
Receipts, collections and the cohort horizon
The models attribute the eventual collected receipts and full delivery cost to the enquiry cohort funded by one period's spend. That is a cohort view, not a same-month cashflow forecast. An aligner course or implant case collected over several months belongs to the month the enquiry arrived for acquisition analysis, while cashflow reporting records each payment in its actual month.
Three rules affect what "collected receipt" means in the UAE:
VAT. Preventive and treatment services by a licensed dentist are zero-rated, while cosmetic services that are neither treatment nor preventive are standard-rated at 5% (PwC Middle East, Jan 2018). Elective cosmetic treatment is not zero-rated unless prescribed to treat or prevent a condition (Gulf News). Veneer and whitening receipts should be entered net of VAT where it applies. No FTA clarification specific to cosmetic dentistry was found (Gulf News).
Insurance. Insurer-quoted annual dental limits are about AED 1,500 to 3,500 with co-payments of about 20%, and brokers say braces and clear aligners are frequently excluded from standard plans (Gulf News; InsuranceMarket.ae). For an insured patient the receipt is split between insurer and patient, and the insurer part depends on approval.
Instalments. Tabby lists dental clinics offering four interest-free instalments, and Tamara offers clinics up to four monthly payments with a 7-day cash settlement. Clinic-run instalment plans spread collection over time; provider-run plans change the fee and settlement terms. Either way the model should use the net amount the clinic receives.
ONS reading Report immature cohorts as immature. Implant and orthodontic cohorts from a 90-day pilot will still have open cases and uncollected receipts at day 90. Assigning all future receipts to the pilot overstates its return; ignoring them understates it. Show collected receipts next to remaining delivery obligations and revisit the cohort when it completes.
Measures that replace the hypothetical inputs
The models become useful when each rate is replaced with a clinic's own aggregated count. The table lists the measure, the denominator and how to read it.
| Measure | Formula or definition | Reading | Source |
|---|---|---|---|
| Media cost per enquiry | Media cost / valid unique enquiries | Acquisition at the enquiry stage only | ONS method [ONS] |
| Qualification rate | Qualified / valid unique enquiries | Fit of targeting and page content | ONS method [ONS] |
| Booking rate | Bookings / qualified enquiries | Availability, response and decision support | ONS method [ONS] |
| Attendance rate | Attended / booked appointments | Access, confirmation and reassurance | ONS method [ONS] |
| Eligibility rate | Clinically eligible / attended assessments | A clinical finding, never a performance quota | ONS method [ONS] |
| Paid-start rate | Paid starts / eligible assessments | Appropriate acceptance and clarity of fees | ONS method [ONS] |
| Fully loaded CAC | (Media + other acquisition) / new paid starts | Cost per new paid case, course or visit | ONS method [ONS] |
| Contribution after acquisition | Collections minus variable delivery minus acquisition cost | Before fixed overhead and tax | ONS method [ONS] |
Keep new patients, existing-patient care, referrals and branch transfers separate. For paediatric work, count adult contacts, unique children and visits separately. A blended revenue-per-lead figure can hide double counting and unfinished care.
ONS reading A service with weak contribution should be improved through clearer enquiry qualification, better attendance, a lower acquisition cost or a different operating model. It should never be improved by pushing clinically inappropriate acceptance or by inflating expected receipts. The eligibility rate is set by clinicians and is not a lever for marketing.
Illustrative monthly resource envelopes
Clinics often ask what a programme costs before any data exist. The envelopes below are ONS resource illustrations, separate from the four treatment models. They are not ONS quotations, observed market fees or a recommended spend for every clinic.
| AED per month (illustration) | Focused branch | Growing portfolio | Several branches | Source |
|---|---|---|---|---|
| Paid media | 18,000 | 40,000 | 75,000 | ONS illustration [ONS] |
| Pages and content | 6,000 | 10,000 | 18,000 | ONS illustration [ONS] |
| CRM and conversion work | 3,000 | 5,000 | 8,000 | ONS illustration [ONS] |
| Measurement | 3,000 | 5,000 | 9,000 | ONS illustration [ONS] |
| Total (sum of rows) | 30,000 | 60,000 | 110,000 | ONS calculation [ONS] |
Paid media is 60.0% of the focused-branch envelope (18,000 / 30,000), 66.7% of the growing-portfolio envelope and 68.2% of the several-branch envelope. For comparison only, one Dubai agency recommends a dental Google Ads budget of AED 4,000 to 10,000 a month, with no method stated (Admoon). Media spend and agency work should be listed separately in any proposal, and shared costs should be allocated by a stated rule rather than loaded onto the best-performing service or left out.
Matching the engagement to the clinic's problem
| Engagement | Included work | Evidence needed before expanding | Source |
|---|---|---|---|
| Branch foundation | Local profile, location page, booking audit, reporting definitions | Reliable routing and attendance data | ONS planning framework [ONS] |
| High-value acquisition | One or two service pathways, search, content, coordinator handoff | Mature eligible cases and contribution | ONS planning framework [ONS] |
| Paediatric and family | Parent pages, first-visit booking, recall measurement | Child attendance and observed continuity | ONS planning framework [ONS] |
| Group growth | Branch governance, shared standards, cohort reporting | Incremental branch contribution and delivery capacity | ONS planning framework [ONS] |
Budgets should follow appointment capacity and the maximum affordable cost of a mature paid case. Spend should rise in measured steps when enquiry relevance, attendance, clinical eligibility and collected contribution stay stable. Chapter 19 sets out the staged plan.
Gaps in the evidence
No public data. No UAE dental cost per lead, cost per click, booking rate, show rate, case acceptance or cost per paid start was found from an independent source; only agency claims for Dubai CPC and one 2011 missed-appointment study. These would sit in clinic CRM and practice-management exports and in ad-platform accounts. A future edition should collect anonymised, aggregated cohort data from consenting clinics in each of Dubai, Abu Dhabi, Sharjah and the other emirates, by service, so the hypothetical inputs can be replaced with observed ranges.
No public data. No split of acquisition economics by emirate exists. The ONS models are not emirate-specific, and the price references used for comparison come from Abu Dhabi, Dubai and Ajman providers only (True Smile, 2026; DentalDate, 2026). Variable delivery costs (laboratory, materials, clinician time) for UAE dental services were not found in any public source, and no UAE data on recall value or retention of paediatric patients was found.
Sources & credits
Admoon, "Google Ads for Dental Clinics Dubai, agency landing page", c. 2024. https://admoon-dubai-growth.lovable.app/google-ads-dental-clinics
Alansaari et al., IJERPH 20, "12", 2023. https://ideas.repec.org/a/gam/jijerp/v20y2023i12p6118-d1170040.html
AlGharebi, Al-Halabi, Kowash et al., European Archives of Paediatric Dentistry 22:29-40, "Children's dental anxiety (self and proxy reported", 2021. https://link.springer.com/article/10.1007%2Fs40368-020-00517-x
Communicate Online, "85 percent of UAE residents want businesses to use WhatsApp", 12 Feb 2024. https://communicateonline.me/news/85-percent-of-uae-residents-want-businesses-to-use-whatsapp/
Communicate, "85 Percent of UAE Residents Want Businesses to Use WhatsApp", 12 Feb 2024. https://communicateonline.me/?p=1277
DentalDate, "Dental price list", Observed 27 October 2026. https://dentaldate.ae/price/
Emirates Specialty Hospital, "Dubai Healthcare City", read 27 Oct 2026. https://emirateshospitals.ae/cost-packages/kids-basic-dental-package/
Enrich Labs, "Average CPC by Industry Google Ads 2026", Undated (2026). https://www.enrichlabs.ai/blog/average-cpc-by-industry-google-ads-2026
Gaidge, "5 Signs Your Dental Aligner Consult Workflow Is Costing You Patients", 26 Sep 2025. https://www.gaidge.com/blog/dental-aligner-consult-workflow
Gulf News, "Will health care services be taxed in UAE?", updated 8 Nov 2018. https://gulfnews.com/your-money/taxation/will-health-care-services-be-taxed-in-uae-1.2145772
Gulf News, 22 Oct 2026. https://gulfnews.com/uae/health/dental-care-in-the-uae-what-families-need-to-know-about-costs-and-insurance-1.500718751
InsuranceMarket.ae, 19 Jun 2026. https://insurancemarket.ae/health-insurance/dental-insurance-dubai/
Ismail AI, Saeed MH, Al-Silwadi FM, J Int Dental and Medical Research 4, "3", 2011. https://research.ajman.ac.ae/en/publications/missed-dental-appointments-in-the-united-arab-emirates/
PwC Middle East, "How VAT impacts you: Healthcare", 2018. https://www.pwc.com/m1/en/tax/vat-in-the-middle-east/pdf/implementation-flyers/how-vat-impacts-you-healthcare.pdf
Search Engine Land citing WordStream by LocaliQ, "Facebook ad costs jump 21% in 2025, but still beat Google", c. Sep 2025 (screenshots dated 2025-09-08). https://searchengineland.com/facebook-ad-costs-jump-beat-google-461690
Tabby, "The Curve Dental Clinic LLC", Accessed Oct 2026. https://tabby.ai/en-AE/merchant/the-curve-dental-clinic
Tamara, "Healthcare Clinics: accelerate growth with Tamara", Live page, fetched 27 Oct 2026. https://tamara.co/en-ae/industry/healthcare
The Dome MedDental Clinic, "JLT", read 27 Oct 2026. https://www.meddental.ae/blog/all-on-4-dental-implants-dubai
Thikaa, "How clinics reduce no-shows by 40% with AI patient communication", 9 Apr 2026. https://thikaa.com/blog/healthcare-patient-communication-ai?lang=en
Thumbay Dental Hospital, "Dental shop listings", Observed 27 October 2026. https://thumbaydentalhospital.com/shop/
True Smile, "Dental treatment price list", Observed 27 October 2026. https://truesmile.ae/price/
Truly Dental, "Dubai dental price list", Observed 27 October 2026. https://trulydental.ae/price-list-dubai
Viva, "Lead Response Time Statistics 2026 for dental practices", 9 Jul 2026. https://www.getviva.ai/lead-response-time-statistics-dental-2026/
VoiceStack compilation, 26 Mar 2026. https://voicestack.com/resources/article/dental-phone-analytics-what-call-data-reveals
VPM International Healthcare, "Ajman Bank member price list", read 27 Oct 2026. https://media.ajmanbank.ae/site/AjmanForLife/documents/VPM-International-PriceList-Dental-English-Approved.pdf
WebTonic, "2026 Dental Google Ads Report", 18 Jul 2026, upd. 9 Oct 2026. https://www.webtonic.io/blog/dental-google-ads-statistics
WordStream / LocaliQ, "Google Ads Benchmarks 2026", 1 April 2025 to 31 March 2026. https://www.wordstream.com/blog/2026-google-ads-benchmarks
PUT THE INSIGHT TO WORK
Your market.
Your next move.
Explore how ONS approaches dental clinic marketing.
Explore our expertise ↗